How AI fits this role
Physical Therapist Assistant in Healthcare & Rehabilitation
Role Overview
Physical Therapist Assistants (PTAs) work under the supervision of licensed Physical Therapists (PTs) to implement treatment plans for patients recovering from injury, surgery, neurological events, or managing chronic musculoskeletal conditions. The role is concentrated in outpatient orthopedic clinics, inpatient rehabilitation hospitals, skilled nursing facilities (SNFs), home health agencies, and school-based therapy programs.
The day-to-day operational reality is hands-on and relational. PTAs guide patients through therapeutic exercise progressions, apply manual therapy techniques, administer modalities such as ultrasound and electrical stimulation, and monitor patient response to treatment. They document session outcomes in electronic health records (EHRs), communicate patient progress to supervising PTs, and adjust exercise intensity based on real-time patient feedback and observable physical response.
In high-volume outpatient settings, a PTA may manage 10–16 patient visits per day. In SNFs, productivity standards are often tied to Medicare reimbursement thresholds, creating constant pressure to document accurately and efficiently while maintaining quality of care. The role sits at the intersection of clinical execution, patient motivation, and administrative compliance — a combination that makes it both difficult to fully automate and increasingly supported by AI-assisted tools.
How AI Is Transforming This Role
The transformation is not about replacing PTAs. It is about restructuring where their time goes and what clinical decisions they are expected to support with data.
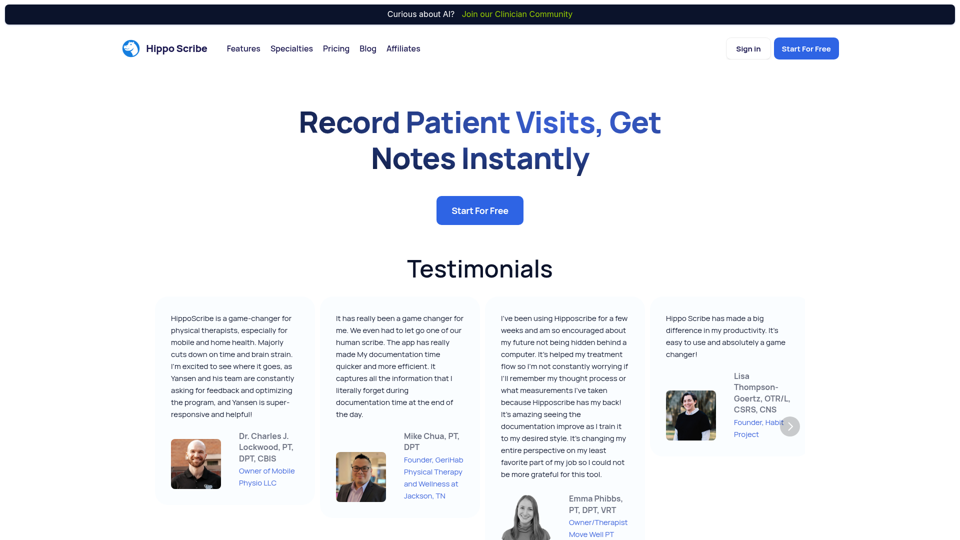
The most immediate shift is in documentation. AI-powered ambient documentation tools — such as those built on large language models integrated into EHR platforms like WebPT, Clinicient, or Raintree — are beginning to transcribe session notes in real time, reducing post-visit charting from 8–12 minutes per patient to under 2 minutes. For a PTA seeing 14 patients daily, this reclaims nearly two hours of administrative time per shift.
The second shift is in outcome tracking. Wearable sensors and motion capture tools are entering outpatient and sports rehab settings, giving PTAs objective gait analysis, range-of-motion measurements, and movement asymmetry data that previously required expensive lab equipment or subjective visual assessment. Platforms like Dorsavi, Hinge Health, and Reflexion Health generate session-by-session biomechanical data that PTAs use to adjust exercise progressions with more precision than observation alone allows.
The third shift is in patient engagement between sessions. AI-driven home exercise program (HEP) platforms — including MedBridge, Kaia Health, and PhysiTrack — now use computer vision through smartphone cameras to monitor patient form during home exercises, flag compensatory movement patterns, and send alerts to the clinical team. PTAs are increasingly responsible for reviewing these between-session data feeds and making protocol adjustments, a task that did not exist in this role five years ago.
Tasks AI Can Automate
- Session note generation: Ambient AI tools transcribe verbal summaries or structured inputs into compliant SOAP or DAP notes, reducing manual documentation burden significantly.
- Home exercise program creation: AI platforms generate individualized HEP libraries based on diagnosis codes, functional limitations, and equipment availability, eliminating manual exercise selection from printed or PDF libraries.
- Outcome measure scoring and trending: Tools like WebPT Outcomes automatically score standardized assessments (LEFS, DASH, PSFS, Oswestry) and generate progress graphs without manual calculation.
- Scheduling optimization: AI-driven scheduling tools flag appointment gaps, predict no-show risk based on patient history, and suggest rebooking windows to maintain visit frequency targets.
- Billing code suggestion: Some EHR platforms now suggest CPT codes based on documented interventions, reducing coding errors and claim denials.
- Movement screening via computer vision: Automated tools can flag gross movement deviations during standardized tests like the Functional Movement Screen or single-leg squat, providing a baseline data point before the PTA conducts hands-on assessment.
Skills Becoming More Valuable
Clinical reasoning under ambiguity. AI tools surface data, but PTAs must interpret it in the context of a patient's pain behavior, psychosocial factors, and motivation. A wearable showing reduced step count does not tell you whether the patient is fearful, fatigued, or non-compliant — that requires conversation and clinical judgment.
Therapeutic alliance and behavioral coaching. Patient adherence to home programs is one of the strongest predictors of rehabilitation outcomes. PTAs who can motivate, educate, and build trust with patients — particularly those with chronic pain, post-surgical anxiety, or low health literacy — deliver outcomes that no AI platform replicates.
Data interpretation and protocol adjustment. As PTAs gain access to objective movement data from wearables and computer vision tools, the ability to translate that data into meaningful exercise progressions becomes a differentiating clinical skill.
Supervision of AI-assisted HEP compliance. Reviewing between-session data feeds, identifying patients who are struggling with home programs, and intervening proactively is an emerging workflow responsibility that requires both clinical knowledge and digital fluency.
Neurological and complex case management. AI tools are weakest in high-variability patient populations — stroke recovery, traumatic brain injury, pediatric developmental conditions. PTAs working in these settings are developing skills that remain deeply human-dependent.
Skills Becoming Less Important
- Manual SOAP note writing from scratch: Ambient documentation tools are making the ability to compose structured clinical notes from memory less critical as a standalone skill.
- Paper-based HEP design: Selecting exercises from printed handout libraries or manually assembling PDF programs is being replaced by AI-curated digital platforms.
- Manual outcome measure calculation: Scoring tools like the Oswestry Disability Index or DASH by hand is increasingly automated within EHR workflows.
- Memorizing CPT code combinations: AI billing assistants embedded in EHRs are reducing the need for PTAs to maintain deep billing code knowledge, though understanding the logic remains important for compliance.
- Scheduling coordination: In larger practices, AI-driven scheduling tools are absorbing the administrative coordination that PTAs and front-desk staff previously managed manually.
Current AI Adoption in This Industry
Adoption is uneven and closely tied to practice size and ownership structure. Large multi-site outpatient groups — particularly those backed by private equity, such as ATI Physical Therapy, Select Medical, or Upstream Rehab — are deploying AI documentation and outcome tracking tools at scale because the ROI on reduced administrative overhead is measurable and immediate.
Independent practices and SNF-based PTAs are adopting more slowly, constrained by EHR switching costs, staff training bandwidth, and tighter margins. In SNFs specifically, the Patient-Driven Payment Model (PDPM) introduced in 2019 shifted Medicare reimbursement away from volume-based billing, reducing some of the productivity pressure that drove early tech adoption in outpatient settings.
Home health is an emerging frontier. AI-powered remote therapeutic monitoring (RTM) codes — introduced by CMS in 2022 — now allow practices to bill for between-session digital monitoring of patient adherence and pain levels. This has accelerated adoption of platforms like Hinge Health, RecoveryOne, and Reflexion Health in home-based and hybrid care models, directly expanding the PTA's role in remote patient oversight.
Wearable-based gait analysis remains largely confined to sports medicine, academic medical centers, and well-funded outpatient orthopedic groups. Broad SNF or home health adoption of motion capture tools is still 3–5 years away from mainstream penetration.
Future Workflow Evolution
The PTA's workflow in 2027–2028 will likely look structurally different from today in three specific ways.
First, the documentation burden will be near-zero for routine visits. Ambient AI will handle note generation, outcome scoring, and billing code suggestion as background processes. PTAs will review and approve rather than compose.
Second, the clinical session itself will be data-informed from the moment the patient walks in. Wearable data from the prior week, HEP adherence rates, pain diary entries, and movement quality scores will be pre-loaded into a session dashboard, allowing the PTA to begin with a targeted clinical question rather than a general check-in.
Third, PTAs in outpatient and home health settings will carry a hybrid caseload — some patients seen in person, others managed primarily through RTM platforms with periodic in-person visits. This model is already operational at Hinge Health and similar digital MSK platforms, where physical therapists and PTAs manage panels of 100–200 patients through a combination of app-based coaching and video visits, with in-person care reserved for cases that do not respond to digital-first protocols.
The supervision ratio between PTs and PTAs may also shift. As AI tools provide more objective data on patient progress, the frequency of PT-PTA case review may decrease for straightforward orthopedic cases, while increasing for complex or non-progressing patients.
Common AI Use Cases
- Ambient clinical documentation (WebPT Assist, Nuance DAX, Suki): Real-time transcription of session interactions into structured EHR notes.
- AI-curated home exercise programs (MedBridge, PhysiTrack, HEP2go with AI layers): Diagnosis-specific exercise selection with video instruction and form feedback.
- Remote therapeutic monitoring (Hinge Health, RecoveryOne, Kaia Health): Between-session adherence tracking, pain logging, and movement quality assessment via smartphone camera.
- Wearable gait and movement analysis (Dorsavi, Noraxon, DARI Motion): Objective biomechanical data capture during functional movement tests and gait assessments.
- Outcome measure automation (WebPT Outcomes, Clinicient Insight): Automated scoring, trending, and benchmarking of standardized patient-reported outcome measures.
- Predictive discharge planning: Some EHR platforms are piloting models that predict expected visit counts to functional discharge based on diagnosis, age, and baseline outcome scores, helping PTAs and PTs set realistic patient expectations early in the episode of care.
Recommended AI Stack
For outpatient orthopedic PTAs:
- WebPT or Clinicient with AI documentation assist for EHR and note generation
- MedBridge for AI-assisted HEP creation and patient education
- PhysiTrack or HEP2go for digital HEP delivery with adherence tracking
- WebPT Outcomes for automated outcome measure scoring
For home health PTAs:
- Kinnser (WellSky) for home health EHR with documentation tools
- Hinge Health or RecoveryOne for RTM-enabled hybrid care models
- A CMS-compliant RTM platform to capture billable between-session monitoring
For sports medicine or high-performance settings:
- Dorsavi or Noraxon for wearable movement analysis
- Hudl Technique or Coach's Eye for video-based movement review
- MedBridge for evidence-based exercise programming
Cross-setting utility:
- Nuance DAX or Suki for ambient documentation if the primary EHR lacks native AI assist
- Microsoft Copilot or similar for administrative tasks — drafting patient communication templates, summarizing research, preparing in-service education materials
Risks & Challenges
Documentation accuracy and liability. AI-generated notes can misrepresent clinical findings if the ambient tool mishears or misinterprets verbal input. PTAs remain legally responsible for the accuracy of signed documentation. Reviewing AI-generated notes carefully is not optional — it is a compliance and liability requirement.
Over-reliance on objective data. Wearable and computer vision tools measure what they can measure. They do not capture pain catastrophizing, fear-avoidance behavior, or the patient who is performing well on metrics but deteriorating psychologically. PTAs who defer too heavily to data risk missing the clinical picture.
Reimbursement complexity with RTM. CMS RTM codes (98975–98977, 98980–98981) have specific requirements around device type, data collection days, and practitioner interaction time. Incorrect billing of RTM services is an active compliance risk, and many practices are still developing internal protocols.
Workforce displacement in administrative-adjacent roles. As AI absorbs scheduling, documentation, and billing support tasks, the administrative staff who supported PTAs in these functions face reduction. PTAs may absorb some of this coordination work directly, increasing cognitive load even as documentation time decreases.
Digital divide in patient populations. RTM and AI-assisted HEP platforms assume smartphone access, digital literacy, and reliable internet connectivity. Elderly patients in SNFs or rural home health populations may not be viable candidates for these tools, creating a two-tier care model within the same practice.
Future Outlook (3–5 Years)
The PTA role will not be automated out of existence. The hands-on, relational, and adaptive nature of physical rehabilitation creates a floor of human necessity that current AI cannot approach. What will change is the composition of the role.
By 2028, PTAs in well-resourced outpatient settings will spend less than 15% of their shift on documentation and administrative tasks, down from the current 25–35%. That reclaimed time will flow into higher patient contact, more complex case management, and expanded responsibilities in remote patient oversight.
The RTM billing model will mature, and hybrid care — combining in-person sessions with AI-monitored home programs — will become the standard of care for common orthopedic conditions like low back pain, knee osteoarthritis, and post-surgical shoulder rehabilitation. PTAs who develop fluency with these platforms will be more productive and more clinically effective than those who do not.
Credentialing and scope of practice questions will intensify. As PTAs take on more data interpretation and remote monitoring responsibilities, professional associations including the APTA will face pressure to clarify what constitutes PT supervision in AI-mediated care models. This is an unresolved regulatory question with real implications for how PTAs are deployed in digital-first practices.
Compensation pressure will remain. The structural economics of physical therapy — high labor cost, insurance reimbursement constraints, and private equity consolidation — mean that productivity expectations will rise alongside AI adoption, not fall. PTAs should expect that efficiency gains from AI tools will be absorbed into larger caseloads rather than reduced hours.
Final Insight
The PTAs who will thrive in the next five years are not the ones who resist AI tools or the ones who defer entirely to them. They are the ones who use ambient documentation to reclaim time, use objective movement data to sharpen clinical decisions, and use that combination to do what the technology cannot: build the therapeutic relationship that makes patients actually do the work.
The clinical core of this role — reading a patient's movement, adjusting in real time, knowing when to push and when to back off, and keeping someone motivated through a painful recovery — is not a workflow problem that AI solves. It is a human skill that AI, used well, gives PTAs more time and better information to practice.